
2026-2027; The Coming Flu Season
Updated: Sep 24
What the Southern Hemisphere has already told us, what New Mexico did last winter, how to choose a vaccine — and this year, how to choose a dose

The view from the south
Flu travels by hemisphere. Australia and New Zealand take their winter while we take our summer, and the viruses that trouble them in July reach us by December. This gives us a few months' warning about which viruses are coming. It tells us nothing, however, about how bad they will be. Forecasting models lose their footing past four weeks, so anyone who tells you in September how bad February will be is guessing.
Last year the warning mattered.
Last year
In July of 2025, Australian labs found a new influenza A(H3N2) and named it subclade K. Its surface protein had changed. It did not match the vaccine. The Australian season, normally twenty weeks, ran thirty-three. Australia counted nearly half a million confirmed cases, the most since records began in 1991, and 1,701 deaths, the worst of the century.
Subclade K reached thirty-four countries. By late January the United States had recorded 280,000 hospitalizations and 12,000 deaths, nearly all from this one variant.
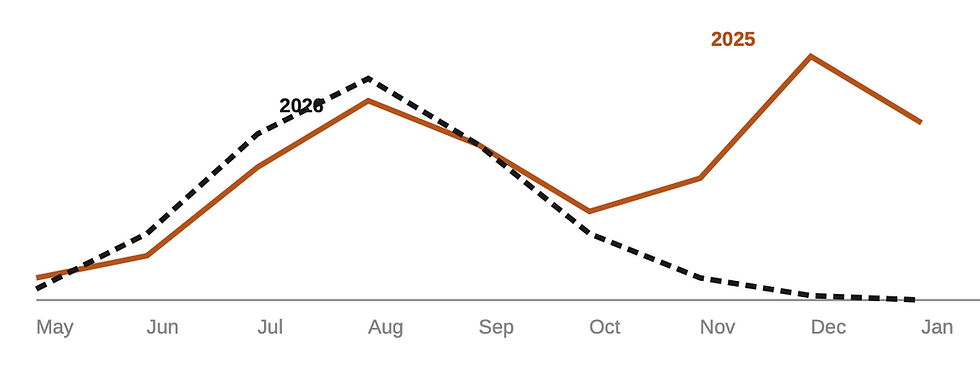
Timing caused the trouble. Subclade K appeared after the vaccine formula was set. A vaccine takes six months to make; a virus drifts in six weeks.
A second reason the vaccine underperformed deserves attention. The immune system remembers the first flu it ever met and keeps reaching for that memory — immune imprinting. When a drifted virus arrives, adults answer it with old antibodies that no longer fit. Children have less to unlearn, and it showed. The vaccine protected three children in four and one adult in three.
What Australia shows now
The southern season is nearly finished, and it reads better. Cases have fallen: 29,300 by early May, half the count at the same date last year. The timing has returned to normal. If that pattern holds as the viruses move north, our peak should fall in the old place, December through February, rather than in early November as it did last year.
H3N2 still leads in both countries. A smaller H3N2 season is still an H3N2 season, and H3N2 is hard on the older population.
Two findings complicate the good news. In Australia, hospital admissions fell while intensive care admissions rose: fewer sick people, more very sick ones. And New Zealand is suffering its worst season for severe illness since 2021, not because of the virus but because vaccine was scarce and the people to give it were scarcer.
The virus sets the ceiling. Coverage decides where beneath it you land.
New Mexico
Three high-severity seasons running would be new territory; the CDC has never recorded it. Two heavy H3N2 seasons have left immunity behind, and this year's vaccine has been rebuilt around subclade K. But the variant continues to evolve, and our exposure has less to do with the virus than with our own numbers.
The season here has not started. PopHIVE's dashboard shows the state at its late-summer floor. PopHIVE scales activity from 0 to 100 and smooths it over three weeks, which makes it a fine instrument for knowing when and a poor one for knowing how many.

The CDC rated New Mexico's influenza activity "Very High" in early January 2026. One winter to the next, flu took a substantially larger share of the state's emergency department traffic. Subclade K accounts for most of the difference.

New Mexico enters this season with roughly half the national vaccination rate, and well under half of Australia's rate among the people flu kills most often. From the last complete season, the state recorded 1,916 flu hospitalizations. Adults 75 and over accounted for a third of them. Seventy-six adults and three children died of influenza.
1 in 3 of New Mexico's flu hospitalizations in 2024–25 were adults 75 and older — the group for whom the stronger vaccines have the best evidence, and the group a 23 percent coverage rate fails.
This year's vaccines
Every product is trivalent: H1N1, an updated H3N2, and B/Victoria. B/Yamagata has not appeared anywhere since March 2020 and has been dropped. Below 65, the CDC prefers no one shot over another.
Vaccine | Type | Ages | Notes |
Afluria, Fluarix, FluLaval, Fluzone | Egg-grown, standard dose | 6 mo+ | The “workhorses” |
Flucelvax | Cell-grown | 6 mo+ | Egg-free |
Flublok
| Recombinant protein | 9 yr+
| Egg-free; triple the antigen |
Fluzone High-Dose | Egg-grown, quadruple antigen | 65+ | Preferred at this age |
Fluad | Adjuvanted (includes an extra ingredient to boost its effectiveness) | 65+ | Preferred at this age |
FluMist | Live, nasal spray | 2-49 | Healthy, not pregnant; can be given at home |
mFLUSIVA | mRNA | 50+ | New |
Choosing a Dose: High, Adjuvanted, or Standard
Age 65 changes the arithmetic. The aging immune system answers a standard shot more faintly than it once did — a fact with a name, immunosenescence, and a remedy that comes in two forms. Fluzone High- Dose simply asks harder: four times the antigen of a standard shot, on the theory that a louder signal reaches a duller ear. Fluad asks differently: a standard dose of antigen, sharpened by an oil-in-water adjuvant that stirs the immune system awake before it examines what it has been given.
Both work better than the standard shot in this age group. A large randomized trial found the high-dose vaccine roughly a quarter more effective than the standard dose at preventing lab-confirmed flu in adults 65 and older. Adjuvanted vaccines have shown a comparable edge in observational studies, though the two products have rarely been tested head-to-head, and neither has been shown to beat the other. Choosing between them is choosing between two hypotheses about the same problem, both supported, neither settled.
What is settled is that a standard dose, for a patient over 65, is no longer the right default. The cost is modest — mild injection-site soreness and fatigue somewhat more often than with a standard shot, nothing worse — and the benefit, in a population that fills a third of the state's flu hospital beds, is not modest at all. Below 65, this reasoning does not apply; the younger immune system needs no louder signal, and a standard dose remains the standard answer.
mRNA or Traditional?
A traditional flu vaccine hands the immune system a piece of virus — grown in eggs, grown in cells, or built as a recombinant protein — and lets the body build its own defenses from that piece. An mRNA vaccine hands the body instructions instead, a scrap of genetic code that directs a person's own cells to manufacture the viral protein on the spot.
The end result looks similar: antibodies against the same surface protein. The manufacturing does not. An mRNA formula can be rewritten in weeks once a new variant is identified; an egg-grown formula needs the better part of a year. Subclade K is the argument for mRNA flu vaccines in miniature — the six months a traditional vaccine needs to update is exactly the six months subclade K used to become unrecognizable.
mFLUSIVA, approved this year for adults 50 and older, is the first mRNA flu vaccine on the market. Set against a standard shot, it prevents one additional case of flu for every 125 people vaccinated — a real benefit, and a small one. It has not been tested against Fluzone High-Dose or Fluad in a trial that measured actual illness; its approval above age 65 rests on antibody levels, a reasonable proxy but not the same evidence the older vaccines carry. It also hurts more at the injection site than a standard shot, and insurance coverage is inconsistent this first year.
For a patient of 50 to 64, where no vaccine is preferred by the CDC, mFLUSIVA is a fair choice, and its manufacturing speed is a genuine advantage if the season drifts again. For a patient over 65, the case is not yet made: High-Dose and Fluad have the trials; mFLUSIVA has the theory. I would offer it, not push it, until it has been measured against the vaccines it hopes to replace.
Eggs nudge the virus to adapt, moving it away from what circulates. H3N2 offends worst. Flucelvax and Flublok avoid eggs, which recommends them in a drift season where supply and cost permit. The evidence suggests this; it does not settle it.
The nasal vaccine, briefly
FluMist works differently from every other product on the list: a live, weakened virus sprayed into the nose rather than a killed one injected into the arm, aiming to raise antibody where flu actually lands rather than in the bloodstream behind it. In theory this should protect better. In American children it has not, reliably — a near-zero effectiveness reading in 2012–14 cost it its recommendation for two seasons, while the same vaccine has held near 60 percent in Britain, and nobody has fully explained the gap.
Its case is narrower than its reputation: no needle, easy to give at home, and a real option for the child who fights the shot or the adult who avoids the clinic to avoid it. Its limits are also narrow: ages two through 49 only, no exception for pregnancy or immune compromise, and an American record that trails the injected vaccine's. For a healthy patient in that age range with a genuine needle phobia and no better option, it beats no vaccine. It is not, this year, a vaccine I would choose over a needle for anyone who will tolerate one.
How well vaccination works
In a well-matched year, the flu shot prevents half of medically attended illness. Last year, against subclade K, it did less.

Poor numbers, honestly reported. They describe how often vaccination prevented an infection, which is not the same question as how often it prevented a catastrophe.
85% of the children who died of flu last season had not been vaccinated. Preventing infection and preventing catastrophe are different jobs, and the vaccine does the second far better. Nearly every complaint of “I got the shot and got sick anyway” confuses them.
Side Effects
Side effects are brief: a sore arm, a headache, some aching, gone in a day or two. The high-dose and adjuvanted versions cause these more often and remain as safe.
Three rarer events deserve mention. Some people faint after a shot, which argues for seating them, not for skipping it. Children under five run a small excess of febrile seizures on the first day. And Guillain- Barré, if it once followed a flu shot within six weeks, calls for a considered conversation rather than a refusal.
When to go
September or October. After last November, September is the safer bet for anyone at real risk.

Miss the window? Get the shot anyway. A late shot beats none, and the virus will still be here.
Sources: New Mexico Department of Health; PopHIVE (Yale School of Public Health); CDC, ACIP, and VRBPAC; UNM Health Sciences Center; Eurosurveillance (Dapat et al., December 2025); Australian Centre for Disease Control; Australian Bureau of Statistics; Doherty Institute; Virology Down Under; interim MMWR effectiveness estimates for 2025–26; manufacturers' prescribing information. Season-shape chart is schematic, drawn from reported timing rather than plotted case counts. This article is general information and does not replace advice about an individual patient.
Comments